
Frozen Shoulder
Introduction

Frozen shoulder, also called adhesive capsulitis, is a condition characterised by painful, and later progressively restricted, active and passive range of motion of the glenohumeral (GH) joint, with external rotation most affected. Terminology is contested (adhesive capsulitis, painful stiff shoulder, periarthritis and idiopathic restriction of shoulder movement are all used) and there are no universally accepted diagnostic criteria.[1][2] The condition is characterised by inflammation and fibrosis of the joint capsule, and early disease can be difficult to distinguish from other causes of a painful shoulder.[3]
Epidemiology
The prevalence of frozen shoulder in the general population is commonly estimated at 2–5%, although reported figures vary according to the population studied and the diagnostic criteria used.[4][5] A German primary care study involving 1,207 practices reported a one-year prevalence of 0.4% and a lifetime prevalence of 2.4% among adults aged 65 years and older, based on recorded diagnoses.[6] Frozen shoulder most commonly affects adults between 40 and 65 years of age.[2][5]
Women appear to account for a greater proportion of diagnosed cases in several large observational studies, although the difference between sexes is not consistent across all populations. A United States database study involving 165,937 patients with adhesive capsulitis reported that 67.2% were women.[7] A Taiwanese population-based study also found a lower risk of developing frozen shoulder among men than women (adjusted hazard ratio 0.69, 95% CI 0.58–0.82).[8] However, a German study of adults aged 65 years and older found similar prevalence estimates between men and women, suggesting that sex differences may vary with age and population characteristics.[6]
Diabetes mellitus is one of the most consistently reported risk factors for frozen shoulder. A 2025 UK cohort study involving 43,977 people with newly diagnosed type 2 diabetes and 43,977 matched individuals without diabetes found that type 2 diabetes was associated with a higher risk of developing frozen shoulder (hazard ratio 4.38, 95% CI 3.70–5.21).[9] Similarly, a 2026 systematic review and meta-analysis reported that people with diabetes had 3.69 times higher odds of developing adhesive capsulitis than those without diabetes (95% CI 2.99–4.56).[5] Earlier evidence also estimated the prevalence of frozen shoulder among people with diabetes at 13.4% (95% CI 10.2–17.2), although estimates vary between studies and diabetic populations.[10]
Frozen shoulder usually affects one shoulder, but the other shoulder may become involved. Previous studies have reported contralateral involvement in approximately 5–34% of cases, although estimates vary and the evidence supporting a single overall frequency remains limited.[11][4]
Pathophysiology
Inflammation and fibrosis
Frozen shoulder is widely regarded as a fibroinflammatory condition involving the shoulder joint capsule. The changes primarily affect the anterosuperior capsule, axillary recess and coracohumeral ligament, with contracture of the rotator interval being a characteristic feature. Although the relative contributions of inflammation, fibrosis and altered neural activity remain under investigation, current evidence supports a process in which synovial inflammation is followed by progressive capsular fibrosis. This involves fibroblast proliferation, differentiation into myofibroblasts, and the accumulation of disorganised type I and type III collagen, alongside changes in extracellular matrix turnover.[1][3][12]
Several inflammatory mediators have been implicated in this process, including interleukin-1 (IL-1), interleukin-6 (IL-6), high mobility group box 1 (HMGB1) and transforming growth factor-beta (TGF-β). These mediators may contribute to persistent inflammation and promote fibrotic tissue changes, while matrix metalloproteinases are involved in extracellular matrix remodelling.[1][12] An imbalance between collagen deposition and tissue remodelling is thought to contribute to capsular thickening, reduced tissue elasticity and contracture of the surrounding ligaments, ultimately restricting shoulder movement.
Emerging evidence
Emerging research suggests that several inflammatory and fibrotic pathways may contribute to the development and persistence of frozen shoulder. Small tissue studies have reported increased IL-17A expression and altered expression of genes involved in inflammation, collagen production and extracellular matrix remodelling, suggesting an interaction between immune responses and fibroblast activity.[13][14]
Recent reviews have also highlighted the potential roles of NF-κB, JAK-STAT, TGF-β/Smad, Wnt/β-catenin and YAP/TAZ signalling pathways in regulating inflammation and fibrosis.[15] These mechanisms may help explain the persistence of capsular contracture even after inflammation subsides. Similarities with Dupuytren's disease and findings from genetic studies further suggest shared mechanisms underlying fibrotic conditions.[16]
Bioinformatics studies have identified candidate genes potentially shared between frozen shoulder and osteoporosis, and between frozen shoulder and Dupuytren's disease.[17][18] However, these findings remain exploratory and require further validation. No validated artificial intelligence tool for diagnosing frozen shoulder or predicting its clinical course was identified in the literature reviewed for this update.
Anatomical Considerations

The glenohumeral joint allows a wide range of shoulder movements, but its bony structures provide relatively little stability on their own. Stability is maintained by the joint capsule, glenohumeral ligaments and glenoid labrum, which provide static support, together with the rotator cuff muscles, which help stabilise the joint during movement.[19] The subscapularis tendon is closely connected to the anterior joint capsule, suggesting that muscle activity may also influence capsular tension.[19] The inferior glenohumeral ligament complex lies beneath the humeral head in a hammock-like arrangement. Its anterior band helps prevent excessive forward and downward movement of the humeral head, particularly when the shoulder is abducted and externally rotated.[19] Cadaveric studies have shown that the capsule and glenohumeral ligaments contribute differently to joint stability depending on the shoulder position and the forces applied. The glenohumeral ligaments are particularly important in resisting anterior and posterior translation of the humeral head.[20] Besides providing mechanical support, the joint capsule and glenoid labrum contain mechanoreceptors that help detect joint position and movement.[21] Signals from these receptors may also trigger reflex responses in the surrounding muscles, helping to coordinate movement and maintain shoulder stability.[22]
Aetiology and Risk Factors
The cause of primary frozen shoulder is not known, and the condition is probably multifactorial, with genetic, metabolic and environmental contributions.[1]
Primary and secondary frozen shoulder
Primary (idiopathic) frozen shoulder has no identifiable cause, whereas secondary frozen shoulder follows a known cause, predisposing factor or surgical event, such as surgery, stroke or injury.[4][11] The terms primary and secondary were introduced by Lundberg in 1969, and secondary frozen shoulder has since been divided into systemic, extrinsic and intrinsic categories.[4] After injury, an altered movement pattern to protect painful structures may change shoulder motor control, reduce range and gradually stiffen the joint.[11]
- Systemic causes include diabetes mellitus and other metabolic conditions.[4][11]
- Extrinsic causes include cardiopulmonary disease, cervical disc pathology, stroke, humeral fracture and Parkinson's disease.[11]
- Intrinsic causes include rotator cuff pathology, biceps tendinopathy, calcific tendinopathy and acromioclavicular joint arthritis, and shoulder surgery may result in an iatrogenic intrinsic form.[4][11]
Metabolic and systemic risk factors
Diabetes is the best established risk factor. A meta-analysis of six case-control studies estimated that people with diabetes had 3.69 times the odds (95% CI 2.99–4.56) of developing frozen shoulder, although unmeasured confounding limits this estimate.[23] Mendelian randomisation analysis within a UK Biobank genome-wide study supported type 1 diabetes as a likely causal risk factor and found no evidence that obesity is causal, which suggests that glycaemic rather than mechanical factors link diabetes and frozen shoulder.[16] Thyroid disorders (hypothyroidism), Dupuytren's disease, Parkinson's disease and stroke are also associated with frozen shoulder.[1] Metabolic syndrome, a cluster of conditions that raises the risk of type 2 diabetes, has also been proposed as a contributor,[24] and people with diabetes tend to respond less well to treatment than people without it.[11] Clinicians should consider screening for diabetes and thyroid disease in patients with frozen shoulder.[2]
Genetic factors
Family and twin studies suggested a genetic contribution.[25] A genome-wide association study of 10,104 cases in the UK Biobank identified five genome-wide significant loci, with considerable overlap with loci associated with Dupuytren's disease,[16] but these are associations that help explain biology and have no current role in clinical diagnosis or management.
Other risk factors
Shoulder injury (a fall on an outstretched hand, direct impact, dislocation), shoulder or other surgery, and complex regional pain syndrome are commonly reported precipitants.[11]
Clinical Presentation
Frozen shoulder typically presents with an insidious onset of increasing pain and gradual loss of active and passive range of motion,[11] and the principal diagnostic finding is reduced passive external rotation.[26] In UK FROST, for example, eligibility required a restriction of at least 50% of passive external rotation in the affected shoulder.[27] Patients often report difficulty with grooming, dressing, overhead reaching and fastening items behind the back, and night pain with disturbed sleep is common.
Sleep
Sleep disturbance is common in frozen shoulder, and nocturnal pain is thought to play an important role in this, with pain, anxiety, depression and reduced quality of life closely related.[28] In a Korean study of 30 patients with idiopathic frozen shoulder and 60 healthy controls, the mean Pittsburgh Sleep Quality Index (PSQI) score was 8.6 in the patient group compared with 4.1 in controls, and the incidence of sleep disturbance was 86.7%.[29] A Turkish study of 76 patients with frozen shoulder and 72 healthy controls likewise found lower sleep efficiency and more sleep disorders in the patient group,[28] and sleep problems appear to be more marked than in subacromial impingement syndrome, with worse sleep latency, sleep duration and sleep disturbance scores in 24 patients with adhesive capsulitis than in 41 patients with impingement.[30] Clinicians should therefore ask about sleep and may consider monitoring it with a validated tool such as the PSQI, which was used in these studies.[29][28]
Phases of frozen shoulder
The condition is commonly described as progressing through three overlapping phases.[3][11][31]
| Phase | Typical features | Commonly quoted duration |
|---|---|---|
| Freezing (painful) | Gradual onset of pain at rest, sharp pain at end range, night pain | About 2–9 months |
| Frozen (stiffening) | Pain eases, progressive loss of GH motion, pain mainly at end range | About 4–12 months |
| Thawing (resolution) | Gradual improvement in functional range | About 5–24 months |
Disease course and prognosis
The disease course, sometimes called the natural history, describes how symptoms change over time without specific treatment. The phases and durations above are descriptive conventions rather than firm natural history, and a systematic review of studies with untreated comparison groups found only low-quality, contradictory evidence and concluded that the idea of a predictable progression to complete resolution without treatment is not supported.[32] Many patients recover well, but a substantial minority report persistent pain or restriction beyond three years,[32] and duration varies widely between individuals, with diabetes associated with a slower recovery.[11][32]
Differential Diagnosis
Several conditions can present with similar pain and stiffness and may also coexist with frozen shoulder, including osteoarthritis, acute calcific bursitis or tendinitis, rotator cuff pathology, Parsonage-Turner syndrome, a locked posterior dislocation and proximal humeral fracture.[11][33]
| Condition | Key distinguishing features |
|---|---|
| Shoulder osteoarthritis | Active range of motion may be limited in abduction and external rotation, but passive range is typically less limited; flexion is often most affected (whereas it is usually least affected in frozen shoulder). Radiographs help rule out osseous pathology. |
| Acromioclavicular joint dysfunction | High arc of pain, pain with cross-body adduction (scarf test), tenderness on palpation of the joint. |
| Bursitis | Can resemble early frozen shoulder, with non-traumatic onset of severe pain. Passive range is usually larger than in frozen shoulder. |
| Parsonage-Turner syndrome | Brachial plexus inflammation; no trauma, painful restriction, pain usually settles faster; weakness or atrophy appears several weeks after onset. |
| Rotator cuff pathology | Restriction does not typically follow the capsular pattern; strength tests may be abnormal or normal early on. MRI or ultrasound can identify soft tissue lesions. |
| Posterior dislocation | Associated with a specific traumatic event; inability to fully supinate the forearm with shoulder flexion raises suspicion. |
| Active muscle guarding (motor control dysfunction) | A 2015 conference abstract reported that all participants with suspected frozen shoulder gained range under anaesthesia, suggesting that some presentations are not explained by capsular contracture alone.[34] A full paper from the same group examined this question further.[35] |
Assessment
Diagnosis is based on history and physical examination, and no specific clinical test or gold standard exists, with imaging generally used to exclude other pathology rather than confirm frozen shoulder.[2][31]
Subjective assessment
A full past medical history (to screen for red flags, diabetes and thyroid disease) and presenting problem history should be taken. Typical features are night pain, pain with sudden or unguarded movements, difficulty lying on the affected side, and reaching overhead or to the side (for example hanging clothes or fastening a seat belt), personal hygiene, dressing and hair brushing are commonly limited. Neck pain often occurs alongside frozen shoulder because the neck muscles have to work harder to compensate for the reduced shoulder movement. [11]
Observation and screening
Posture and scapular position can be observed, and scapular winging may be visible. An upper quarter screen and neurological screen (dermatomes, myotomes, reflexes) excludes cervical or neurological pathology.[11]
Range of movement
The range of motion of the cervical spine, thoracic spine and shoulder should be assessed, including the use of overpressure when appropriate. Rib mobility should also be examined. In frozen shoulder, movements such as flexion, abduction, external rotation and internal rotation are often limited. Patients may also use compensatory movements of the scapula to help raise the arm. External rotation is typically the most restricted movement in the classic capsular pattern of frozen shoulder.[36]
Glenohumeral ligaments and accessory movements
Assessing accessory movement gives an indication of global joint stiffness and should be compared with the contralateral side, remembering that the other shoulder may not be normal, and both the quality and quantity of movement matter. Strain within the capsuloligamentous complex changes with arm position, and in a cadaveric study of passive rotation the inferior capsule, particularly its anterior part, had a significant influence on internal and external rotation at 60° of abduction in the scapular plane, while the superior and posterior regions contributed less than previously thought.[37] In frozen shoulder the anterior and inferior capsule tend to be the most restricted, although joint mobility is reduced in all directions.[36] Flexion, internal rotation and horizontal flexion are coupled with anterior-superior translation of the humeral head, and extension, external rotation and abduction with external rotation are coupled with posterior translation (see arthrokinematics).
| Structure | Function | Assessment (patient supine, scapula stabilised, arm by side unless stated) |
|---|---|---|
| Superior GH ligament and coracohumeral ligament | Superior: stabilises in adduction, limits external rotation and inferior translation. Coracohumeral: anterior portion limits extension, posterior portion limits flexion; also limits inferior and posterior translation | Take passive external rotation to end range, apply an anterior glide to the humeral head (posterior and lateral bands). Adding 10° extension assesses the anterior and medial band of the coracohumeral ligament |
| Middle GH ligament | Stabilises in adduction plus external rotation, and in about 45° abduction with external rotation | 10° extension, external rotation to end range, then 45° abduction with an antero-medial glide in the plane of the scapula; compare sides |
| Inferior GH ligament, anterior band | Stabilises in abduction and external rotation | Move from the previous position towards 90° abduction with external rotation, apply an anterior-medial glide. Use caution if instability is suspected, as this resembles the apprehension test |
| Inferior GH ligament, posterior band | Posterior stability in abduction and internal rotation | 90° abduction, 10° extension, full internal rotation, gentle anterior-lateral glide |
| Posterior capsule | Posterior restraint | 90° flexion, full internal rotation, end-range horizontal adduction; apply an axial stress in a posterior-lateral direction in the plane of the scapula (similar to testing for posterior instability) |
Tightening of the superior GH ligament and coracohumeral ligament can alter arthrokinematics, increasing anterior-superior translation in flexion and reducing the subacromial space.
Resisted tests
Resisted external rotation, internal rotation and abduction can be tested seated, and weakness relative to the unaffected side and significant muscle guarding may be present,[11] so the stage and irritability of the condition should be considered before resisted testing.
Functional and special tests
The shoulder shrug sign (inability to elevate the arm to 90° abduction without elevating the shoulder girdle) is associated with frozen shoulder, glenohumeral arthritis and massive cuff tears.[38] Three function-related tests (hand to neck, hand to scapula and hand to opposite scapula, the scarf test) have excellent reliability and moderate inter-test correlation, although a direct relationship with activities of daily living should not be assumed, and these tests need adequate elbow, scapulothoracic and thoracic mobility.[39]

Psychosocial factors
Pain-related beliefs appear to influence how people with frozen shoulder experience pain and disability, so an assessment that concentrates only on range of motion may miss factors that shape recovery. In a cross-sectional study of 85 people with frozen shoulder, higher pain-related fear (Tampa Scale for Kinesiophobia, TSK-11) and higher pain catastrophising were associated with poorer arm function on the DASH, whereas higher pain self-efficacy was associated with better function, with self-efficacy showing the strongest association (r = −0.69); adding these three beliefs to a model containing pain intensity explained a further 26% of the variance in arm function.[40] A more recent cross-sectional study reported that higher pain self-efficacy was associated with lower activity-related pain and disability on the SPADI, that higher kinesiophobia and body mass index were associated with greater disability, and that higher anxiety was associated with greater activity-related pain, while depression, pain catastrophising and sleep quality were not associated with either outcome in that sample.[41] A systematic review likewise concluded that scores traditionally regarded as physical measures of pain, function and disability appear to be influenced by psychological variables, and that pain-related fear and catastrophising appear to be associated with perceived arm function.[42]
These beliefs can be screened with brief questionnaires, such as the 10-item Pain Self-Efficacy Questionnaire (PSEQ, scored 0–60, with higher scores indicating greater confidence in performing activities despite pain)[43] or its two-item short form,[44] together with the TSK-11 for fear of movement, which has been examined alongside the Fear-Avoidance Beliefs Questionnaire in people with shoulder pain.[45] Because the evidence cited here is cross-sectional, it shows associations rather than cause and effect, and it remains unclear whether targeting these beliefs improves outcomes in frozen shoulder specifically. A low self-efficacy score or a high fear score can nevertheless help to guide education, pacing and graded exposure to movement within the stage-based approach described under Management, and the scores are best interpreted together with pain intensity, sleep and functional measures.
Outcome Measures
| Outcome measure | Domain |
|---|---|
| Shoulder Pain and Disability Index (SPADI) | Shoulder-specific pain and disability |
| Disabilities of the Arm, Shoulder and Hand (DASH) | Upper limb function |
| American Shoulder and Elbow Surgeons (ASES) score | Shoulder pain and function |
| Simple Shoulder Test (SST) | Shoulder function |
| Penn Shoulder Score (PSS) | Pain, satisfaction and function |
| NPRS, VAS | Pain intensity |
| SF-36 | Health-related quality of life |
| Pittsburgh Sleep Quality Index, MOS-Sleep | Sleep |
| Pain Self-Efficacy Questionnaire (PSEQ, PSEQ-2) | Confidence in performing activities despite pain |
| Tampa Scale for Kinesiophobia (TSK-11) | Pain-related fear of movement |
The psychometric properties of SPADI, DASH, ASES and SST are favourable across shoulder disorders, although a systematic review did not examine them specifically in frozen shoulder.[46]
Management
A review concluded that non-surgical and rehabilitative interventions are effective for frozen shoulder, but found no evidence that one approach is more effective than another, and called for higher-quality trials with standardised intervention content.[47] In clinical practice, management should be individualized according to the stage of frozen shoulder, symptom irritability, the person's functional needs and any associated conditions, such as diabetes. Early management should focus on pain relief and improving sleep, with exercise intensity and other interventions adjusted to the person's tolerance.
Education and self-management
Patient education is an important part of frozen shoulder management. Patients should understand that recovery can be slow, stiffness may gradually improve over time, and full shoulder movement may not always return. Recovery may take longer in people with diabetes. Providing realistic expectations can help reduce frustration and encourage continued participation in rehabilitation.
A simple, individualised home exercise programme is a key part of rehabilitation. Regular practice helps patients maintain shoulder movement and work towards improving function. A network meta-analysis found that combining intra-articular corticosteroid injection with a home exercise programme provided additional benefits for pain relief in the medium term compared with injection alone.[48]
As frozen shoulder can cause persistent pain and emotional distress, self-management may also include relaxation techniques, controlled breathing and gradual exposure to movements that cause discomfort. These strategies may help patients manage pain-related fear, improve confidence in moving the shoulder and remain active during recovery.
Stage-based physiotherapy
Physiotherapy for frozen shoulder is often guided by the stage of the condition. However, this stage-based approach is mainly based on older studies and expert consensus rather than a well-established treatment protocol.[11][49]
Freezing phase (high irritability)
During this phase, the main priorities are pain relief. Exercises should be gentle, low intensity and performed within a comfortable range to avoid aggravating symptoms. Suitable exercises include pendulum exercises, supported passive shoulder flexion, passive external rotation with the shoulder positioned at approximately 40° of abduction in the scapular plane, and active-assisted shoulder movements. Movements can be held for one to five seconds and repeated several times throughout the day, provided they remain pain-free.[11]
Applying heat before or during treatment may help patients perform stretching exercises more comfortably.[11] Evidence also suggests that simple, pain-free exercises may produce better outcomes than intensive therapy during this stage.[3] Gentle joint mobilisation, using Maitland grades I–II, is commonly used to help manage pain.
Frozen phase (stiffening)
As pain and irritability become more manageable, physiotherapy can place greater emphasis on improving shoulder mobility. Stretching and joint mobilisation can be progressed gradually according to the patient's tolerance, while avoiding excessive force that may aggravate symptoms.
Treatment may include end-range joint mobilisation and mobilisation with movement. One trial reported better outcomes with mobilisation with movement than with stretching alone.[50] Another study found that end-range mobilisation was more effective than mid-range mobilisation in improving shoulder movement and function.[51] A randomised trial also found that high-grade mobilisation (Maitland grades III–IV) produced greater improvements in passive shoulder abduction at three and 12 months, as well as active and passive external rotation at 12 months, compared with low-grade mobilisation.[52] A small trial further reported greater improvements in external rotation with posterior glide than with anterior glide mobilisation.[53]
Other approaches have also been investigated. Positional stretching of the coracohumeral ligament has been described in a single case report, while a controlled cohort study reported improved active external rotation when dynamic splinting was combined with physiotherapy compared with either intervention alone.[54] These findings should be interpreted cautiously because the studies are small, and many were conducted more than a decade ago.
Thawing phase (resolution)
During the thawing phase, pain and irritability generally decrease, allowing stretching exercises to be performed more frequently and held for longer periods. Stretching intensity can be increased gradually, alongside strengthening exercises targeting the rotator cuff and scapular stabilizing muscles. These exercises aim to maintain improvements in shoulder mobility, restore muscle control and support the return to functional activities.[11]
The amount of stretching required varies between individuals. Decisions about progressing or discharging a patient should therefore consider more than shoulder range of motion alone. Pain reduction, changes in mobility over time, functional improvement and the patient's satisfaction with recovery should also guide clinical decisions.[11]
-
 Active assisted end-range movements in flexion, external rotation and extension.
-
 Active assisted end-range movements in internal rotation, horizontal adduction and flexion.
-
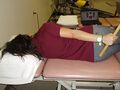 Coracohumeral ligament stretch.
-
 Active assisted movements in elevation and external rotation with a cane.
-
 Posterior mobilisations of the humeral head in supine.
-
 Anterior mobilisations of the humeral head in supine.


Evidence for physiotherapy interventions
| Intervention | Evidence and effect | Outcomes | Certainty and limitations | Key evidence |
|---|---|---|---|---|
| Education and home exercise | Adding a simple home exercise programme to intra-articular corticosteroid gave additional mid-term benefit | Pain, function | Moderate; mostly studied as an adjunct to injection | Challoumas 2020[48] |
| Structured physiotherapy plus steroid injection | In secondary care, none of the three pathways was superior on the Oxford Shoulder Score at 12 months; serious adverse events occurred only in the surgical arms (8 with capsular release, 2 with manipulation under anaesthesia) | Function, quality of life, cost | Moderate to high (pragmatic RCT, n = 503); applies to a specific 12-session protocol | UK FROST, Rangan 2020[27] |
| Exercise (stretching, mobility) | Pooled analysis of pre-post change found large improvements in ROM, function and pain, with larger ROM gains when joint mobilisation was added | ROM, function, pain | Low: pooled within-group change rather than controlled comparisons, high heterogeneity, unregistered protocol | Lee 2023[55] |
| Manual therapy plus exercise | Cochrane review found no trial against placebo or no treatment, and heterogeneous comparisons; may be less effective than steroid injection in the short term | Pain, function, ROM | Low; this review is from 2014 | Page 2014[56] |
| Joint mobilisation | High-grade mobilisation improved range more than low-grade at 3 to 12 months in one RCT; further trials on type and direction are small | ROM, disability | Low; small older trials | Vermeulen 2006[52] |
| Scapulothoracic physiotherapy | Pooled moderate to large effect favouring scapulothoracic interventions; no significant between-group difference in pain | Shoulder function, pain | Low to moderate; considerable heterogeneity | 2026 systematic review and meta-analysis[57] |
| Therapeutic ultrasound | No evidence of greater improvement in abduction than placebo; findings for other outcomes inconsistent | Pain, ROM, disability | Low; five studies in meta-analysis | Sung 2022[58] |
| Extracorporeal shockwave therapy | Authors report evidence of pain reduction in chronic frozen shoulder with type 2 diabetes | Pain | Low; seven studies, one subpopulation | Reno 2025[59] |
| Intra-articular corticosteroid plus physiotherapy | Corticosteroid gave the greatest short-term benefit (about 1 VAS point for pain versus no treatment or physiotherapy), lasting up to 6 months in early disease. Steroid plus physiotherapy was most beneficial in the freezing phase | Pain, function | Moderate; benefit greatest for symptoms under 1 year | Challoumas 2020[48]; Zhang 2021[60] |
| Hydrodilatation with or without physiotherapy | Conflicting: a 2023 meta-analysis found a transient disability benefit over steroid alone (SMD 0.24) and no difference from manipulation, capsular release or general physiotherapy. A 2026 review of 44 RCTs found greater external rotation at 12 weeks (low certainty) but no difference in pain or SPADI and concluded it does not support meaningful benefit over steroid alone or as an adjunct to physiotherapy | Pain, disability, ER | Low; variable technique, volume and capsule rupture | Poku 2023[61]; 2026 review[62] |
Modalities and other approaches
Heat and cold have been used with exercise, and hot and cold packs before and after exercise were reported to improve outcomes in a randomised study that also used steroid injection.[63] A retrospective cohort study reported that ultrasound, massage, iontophoresis and phonophoresis were associated with a reduced likelihood of improvement,[64] and a 2022 meta-analysis of ultrasound found no consistent benefit over placebo.[58] Acupuncture, dry needling, kinesiology taping and proprioceptive neuromuscular facilitation are used clinically, but their effects were not appraised in this update (a 2019 meta-analysis concluded that PNF reduced pain and improved range and function),[65] and a Cochrane review of physiotherapy for shoulder pain found no evidence of an effect of ultrasound in frozen shoulder.[66]
Injection and Interventional Management
Corticosteroid injection
Corticosteroid injections are commonly used during the early, painful stage of frozen shoulder to reduce inflammation and relieve pain. A network meta-analysis of 65 studies found that intra-articular corticosteroid injections provided better short-term pain relief and functional improvement than other treatments. Pain scores improved by approximately 1.0 point on the visual analogue scale (VAS) compared with no treatment and 1.1 points compared with physiotherapy. These benefits could last up to six months, particularly in patients whose symptoms had been present for less than one year.[48] Another network meta-analysis found that combining corticosteroid injection with physiotherapy was particularly beneficial during the freezing phase.[60]
Earlier reviews also reported that corticosteroid injections provided greater symptom relief than physiotherapy in the short term, particularly at four to six weeks. However, the difference between treatments became smaller by 12 weeks.[67][68] Both subacromial and intra-articular injections have been reported to produce similar outcomes.
Corticosteroid injections should be used with caution in patients with infection, coagulation disorders or uncontrolled diabetes. In people with diabetes, corticosteroids may temporarily increase blood glucose levels. Therefore, injections should be considered alongside an appropriate exercise programme rather than used as a standalone treatment.[48]
Hydrodilatation (distension arthrography)
Hydrodilatation instils a large volume (often about 30 mL) of saline, steroid and local anaesthetic into the joint under imaging guidance. The role of capsular rupture is unclear, and systematic reviews disagree on benefit over corticosteroid alone (see table).[61][62][69]
Other injections and oral drugs
NSAIDs have been used, but high-level evidence for effectiveness is lacking.[3][68] Oral corticosteroids have short-term benefits only and are not recommended routinely,[70] and suprascapular nerve block has been used for pain, with some evidence of benefit but unclear mechanism.[68]
Surgical management
Surgical options are generally considered after at least about 6 months of unsuccessful conservative treatment, although no studies have established the best time to switch.[11][68]
United Kingdom Frozen Shoulder Trial (UK FROST)
UK FROST was the largest randomised controlled trial comparing treatments for primary frozen shoulder, involving 503 participants. Earlier trials generally included between 26 and 136 participants. Conducted across 35 National Health Service hospitals, this pragmatic, multicentre trial included adults with unilateral frozen shoulder, defined as at least a 50% reduction in passive external rotation of the affected shoulder. The participants had a mean age of 54 years, and 63% were female.[27]
Participants were randomly assigned in a 2:2:1 ratio to one of three treatment approaches: manipulation under anaesthesia (MUA) followed by a steroid injection, arthroscopic capsular release followed by manipulation, or early structured physiotherapy combined with a steroid injection. Arthroscopic capsular release involves surgically releasing the contracted anterior capsule around the rotator interval, followed by manipulation to improve shoulder movement. The main outcome was the Oxford Shoulder Score, a 12-item questionnaire assessing pain and shoulder function, measured at 12 months. Scores range from 0 to 48.[27]
At 12 months, no treatment showed clear superiority over the others in patient-reported outcomes, although arthroscopic capsular release may provide a small clinically meaningful benefit over physiotherapy. However, capsular release was associated with more serious adverse events than MUA (eight compared with two) and higher treatment costs. Despite these risks, fewer patients who underwent capsular release required further treatment. When cost-effectiveness was assessed using a threshold of £20,000 per quality-adjusted life-year, MUA had the highest probability of being cost-effective, at 0.86. The trial investigators therefore recommended reserving capsular release for selected patients who have not improved with less invasive and less costly treatments.[27]
Manipulation under anaesthesia (MUA)
MUA involves controlled end-range positioning of the humerus under a brachial plexus block, now using short rather than long lever arms. Risks include fracture, dislocation, nerve injury, rotator cuff tear and haemarthrosis,[11][71] and contraindications include previous fracture or dislocation, significant bone loss and inability to follow post-procedure care. Translation mobilisation under anaesthesia has been proposed as a safer alternative, but evidence is limited.[11]
Arthroscopic capsular release
Arthroscopic capsular release selectively releases the contracted capsule (most commonly the rotator interval and coracohumeral ligament) and avoids some MUA complications. It is the most widely used procedure for refractory frozen shoulder and is often favoured in diabetes and in post-operative or post-fracture frozen shoulder, although direct comparisons are few.[11][68]
Post-surgical considerations
Physiotherapy after surgery should be started promptly and individualised.[27] Nerve integrity near portal sites (axillary, suprascapular, musculocutaneous, radial, median, ulnar and long thoracic nerves and the brachial plexus) should be considered, because sudden restoration of movement after months of stiffness may irritate nerves, and the cervical spine and nerve root mobility should also be assessed.
Clinical Considerations and Red Flags
Red flag screening should be included in every initial assessment of a patient with a painful, stiff shoulder. Although frozen shoulder can cause significant pain and restricted movement, similar symptoms may also occur in more serious conditions, including malignancy, infection and fracture.
Features that warrant further investigation or urgent referral include fever, night sweats, unexplained weight loss, new respiratory symptoms, an abnormal joint shape, a localised mass or swelling, redness over a hot and tender joint, sudden symptoms following trauma, or severe restriction of shoulder movement. A history of malignancy, particularly lung or breast cancer, should also be considered during the assessment.[26]
A published case series describing malignant tumours of the shoulder girdle that were initially misdiagnosed as frozen shoulder highlights the importance of considering alternative diagnoses when symptoms or clinical findings are atypical.[72] Pain affecting other joints may also indicate osteoarthritis or a systemic inflammatory condition, such as rheumatoid arthritis.[26] Further information on identifying and managing clinical warning signs is available on the flag system page.
Secondary frozen shoulder requires additional consideration when it occurs following a stroke or alongside complex regional pain syndrome (CRPS). In these cases, the underlying condition may influence the patient's presentation, functional limitations and rehabilitation approach, so management should be tailored accordingly.[11]
Clinical Bottom Line
No intervention has clearly superior evidence, and treatment should match the stage, irritability, comorbidity and preferences of the individual. Early pain control and sleep support, education and a home programme are core, and for people with high pain levels in early disease, corticosteroid injection combined with structured physiotherapy has the strongest comparative evidence.[27][48][60] Surgical options are generally reserved for people who remain disabled despite conservative care, with MUA and capsular release producing outcomes comparable to physiotherapy plus injection in the largest trial.[27] The cause and disease course remain incompletely understood, and the aim in clinical practice is to focus on the quality of movement and function rather than range alone.
References
- ↑ 1.0 1.1 1.2 1.3 1.4 Millar NL, Meakins A, Struyf F, Willmore E, Campbell AL, Kirwan PD, et al. Frozen shoulder. Nat Rev Dis Primers. 2022;8(1):59.
- ↑ 2.0 2.1 2.2 2.3 Ramirez J. Adhesive capsulitis: diagnosis and management. Am Fam Physician. 2019;99(5):297-300.
- ↑ 3.0 3.1 3.2 3.3 3.4 Dias R, Cutts S, Massoud S. Frozen shoulder. BMJ. 2005;331:1453-6.
- ↑ 4.0 4.1 4.2 4.3 4.4 4.5 Lewis J. Frozen shoulder contracture syndrome - aetiology, diagnosis and management. Man Ther. 2015;20(1):2-9.
- ↑ 5.0 5.1 5.2 Hernigou, P., & Scarlat, M. M. (2026). The diabetic shoulder: Association between diabetes mellitus and adhesive capsulitis—A systematic review and meta-analysis. International Orthopaedics, 50, 839–851. https://doi.org/10.1007/s00264-026-06793-4
- ↑ 6.0 6.1 Jacob L, Gyasi R, Koyanagi A, Haro JM, Smith L, Kostev K. Prevalence of and risk factors for adhesive capsulitis of the shoulder in older adults from Germany. J Clin Med. 2023;12(2):669.
- ↑ Cogan CJ, Cevallos N, Freshman RD, Lansdown D, Feeley BT, Zhang AL. Evaluating utilization trends in adhesive capsulitis of the shoulder: a retrospective cohort analysis of a large database. Orthop J Sports Med. 2022;10:23259671211069577.
- ↑ Huang SW, Lin JW, Wang WT, Wu CW, Liou TH, Lin HW. Hyperthyroidism is a risk factor for developing adhesive capsulitis of the shoulder: a nationwide longitudinal population-based study. Sci Rep. 2014;4:4183.
- ↑ Dyer, B. P., Burton, C., Rathod-Mistry, T., Blagojevic-Bucknall, M., & van der Windt, D. A. (2025). Type 2 diabetes, metabolic health, and the development of frozen shoulder: A cohort study in UK electronic health records. BMC Musculoskeletal Disorders, 26, 471. https://doi.org/10.1186/s12891-025-08672-2
- ↑ Zreik NH, Malik RA, Charalambous CP. Adhesive capsulitis of the shoulder and diabetes: a meta-analysis of prevalence. Muscles Ligaments Tendons J. 2016;6:26-34.
- ↑ 11.00 11.01 11.02 11.03 11.04 11.05 11.06 11.07 11.08 11.09 11.10 11.11 11.12 11.13 11.14 11.15 11.16 11.17 11.18 11.19 11.20 11.21 11.22 11.23 11.24 Kelley MJ, McClure PW, Leggin BG. Frozen shoulder: evidence and a proposed model guiding rehabilitation. J Orthop Sports Phys Ther. 2009;39:135-48.
- ↑ 12.0 12.1 Kraal T, Lubbers J, van den Bekerom MPJ, Alessie J, van Kooyk Y, Eygendaal D, et al. The puzzling pathophysiology of frozen shoulders - a scoping review. J Exp Orthop. 2020;7:91.
- ↑ Akbar M, Crowe LAN, McLean M, Garcia-Melchor E, MacDonald L, Carter K, et al. Translational targeting of inflammation and fibrosis in frozen shoulder: molecular dissection of the T cell/IL-17A axis. Proc Natl Acad Sci U S A. 2021;118(39):e2102715118.
- ↑ Nishimoto et al. Characteristics of gene expression in frozen shoulder. BMC Musculoskelet Disord. 2022;23:811.
- ↑ Guo T, Hua Y, Liu X, Hu B, Wang C, He J, et al. Signaling pathway networks in frozen shoulder fibrosis: from inflammatory initiation to fibrotic progression. Front Med (Lausanne). 2026;13:1883535.
- ↑ 16.0 16.1 16.2 Green HD, Jones A, Evans JP, Wood AR, et al. A genome-wide association study identifies 5 loci associated with frozen shoulder and implicates diabetes as a causal risk factor. PLoS Genet. 2021;17:e1009577.
- ↑ Identification of common genetic features and pathways for osteoporosis with frozen shoulder by integrated bioinformatics analysis and machine learning. PMID 41276899.
- ↑ Ouyang Y, Chen S, Tu Y, Wan T, Fan H, Sun G. Exploring the potential relationship between frozen shoulder and Dupuytren's disease through bioinformatics analysis and machine learning. Front Immunol. 2023;14:1230027.
- ↑ 19.0 19.1 19.2 Gasbarro G, Bondow B, Debski R. Clinical anatomy and stabilizers of the glenohumeral joint. Annals of Joint. 2017;2:58. https://doi.org/10.21037/aoj.2017.10.03
- ↑ Debski RE, Wong EK, Woo SL-Y, Sakane M, Fu FH, Warner JJP. In situ force distribution in the glenohumeral joint capsule during anterior-posterior loading. Journal of Orthopaedic Research. 1999;17(5):769–776. https://doi.org/10.1002/jor.1100170523
- ↑ Witherspoon JW, Smirnova IV, McIff TE. Neuroanatomical distribution of mechanoreceptors in the human cadaveric shoulder capsule and labrum. Journal of Anatomy. 2014;225(3):337–345. https://doi.org/10.1111/joa.12215
- ↑ Myers JB, Lephart SM. Sensorimotor deficits contributing to glenohumeral instability. Clinical Orthopaedics and Related Research. 2002;(400):98–104. https://doi.org/10.1097/00003086-200207000-00013
- ↑ Dyer BP, Rathod-Mistry T, Burton C, van der Windt D, Bucknall M. Diabetes as a risk factor for the onset of frozen shoulder: a systematic review and meta-analysis. BMJ Open. 2023;13:e062377.
- ↑ Pietrzak M. Adhesive capsulitis: an age related symptom of metabolic syndrome and chronic low-grade inflammation? Med Hypotheses. 2016;88:12-7.
- ↑ Hakim AJ, Cherkas LF, Spector TD, MacGregor AJ. Genetic associations between frozen shoulder and tennis elbow: a female twin study. Rheumatology (Oxford). 2003;42:739-42.
- ↑ 26.0 26.1 26.2 Artus M, Holt TA, Rees J. The painful shoulder: an update on assessment, treatment, and referral. Br J Gen Pract. 2014;64(626):e593-5.
- ↑ 27.0 27.1 27.2 27.3 27.4 27.5 27.6 27.7 Rangan A, et al. Management of adults with primary frozen shoulder in secondary care (UK FROST): a multicentre, pragmatic, three-arm, superiority randomised clinical trial. Lancet. 2020;396(10256):977-89.
- ↑ 28.0 28.1 28.2 Toprak M, Erden M. Sleep quality, pain, anxiety, depression and quality of life in patients with frozen shoulder. J Back Musculoskelet Rehabil. 2019;32(2):287-91.
- ↑ 29.0 29.1 Cho CH, Son ES, Hwang IS, Jung SW. Sleep status and quality of life in patients with frozen shoulder. J Korean Orthop Assoc. 2012:205-10.
- ↑ Çağlar Yağcı H, Gençer Atalay K, Kaplan E, Yağcı İ. Nocturnal pain in adhesive capsulitis and subacromial impingement syndrome. Int J Res Med Sci. 2023;11(9):3189-94.
- ↑ 31.0 31.1 Walmsley S, Rivett DA, Osmotherly PG. Adhesive capsulitis: establishing consensus on clinical identifiers for stage 1 using the Delphi technique. Phys Ther. 2009;89:906-17.
- ↑ 32.0 32.1 32.2 Wong CK, et al. Natural history of frozen shoulder: fact or fiction? A systematic review. Physiotherapy. 2017;103:40-7.
- ↑ Kline CM. Adhesive capsulitis: clues and complexities. JAMA. 2007. .
- ↑ Hollmann L, Halaki M, Haber M, Herbert R, Dalton S, Ginn K. Determining the contribution of active stiffness to reduced range of motion in frozen shoulder. Physiotherapy. 2015;101:e585.
- ↑ Hollmann L, Halaki M, Kamper SJ, Haber M, Ginn KA. Does muscle guarding play a role in range of motion loss in patients with frozen shoulder? Musculoskelet Sci Pract. 2018;37:64-8.
- ↑ 36.0 36.1 Mitsch J, Casey J, McKinnis R, Kegerreis S, Stikeleather J. Investigation of a consistent pattern of motion restriction in patients with adhesive capsulitis. J Man Manip Ther. 2004;12:153-9.
- ↑ Kim SY, Chang M, Chae SW. Three-dimensional comparative strain analysis of the capsuloligamentous complex during passive glenohumeral motion. J Orthop Surg Res. 2025;21(1):1-17.
- ↑ Jia X, Ji JH, Petersen SA, Keefer J, McFarland EG. Clinical evaluation of the shoulder shrug sign. Clin Orthop Relat Res. 2008;466(11):2813-9.
- ↑ 39.0 39.1 Yang J, Lin J. Reliability of function-related tests in patients with shoulder pathologies. J Orthop Sports Phys Ther. 2006;36:572-6.
- ↑ De Baets L, Matheve T, Traxler J, Vlaeyen J, Timmermans A. Pain-related beliefs are associated with arm function in persons with frozen shoulder. Shoulder Elbow. 2020;12(6):432-40.
- ↑ Fonseca RNS, Policastro PO, Medeiros Filho JF, Lucena EMF, Kamonseki DH, Barbosa GM. Association of psychological factors and sleep quality with activity-related pain and disability in individuals with frozen shoulder. Musculoskelet Sci Pract. 2025:103366.
- ↑ Brindisino F, Silvestri E, Gallo C, Venturin D, Di Giacomo G, Peebles AM, et al. Depression and anxiety are associated with worse subjective and functional baseline scores in patients with frozen shoulder contracture syndrome: a systematic review. Arthrosc Sports Med Rehabil. 2022;4(3):e1219-34.
- ↑ Nicholas MK. The pain self-efficacy questionnaire: taking pain into account. Eur J Pain. 2007;11(2):153-63.
- ↑ Nicholas MK, McGuire BE, Asghari A. A 2-item short form of the pain self-efficacy questionnaire: development and psychometric evaluation of PSEQ-2. J Pain. 2015;16(2):153-63.
- ↑ Mintken PE, Cleland JA, Whitman JM, George SZ. Psychometric properties of the Fear-Avoidance Beliefs Questionnaire and Tampa Scale of Kinesiophobia in patients with shoulder pain. Arch Phys Med Rehabil. 2010;91(7):1128-36.
- ↑ Roy J, MacDermid J, Woodhouse L. Measuring shoulder function: a systematic review of four questionnaires. Arthritis Rheum. 2009;61(5):623-32.
- ↑ de Sire A, Agostini F, Bernetti A, et al. Non-surgical and rehabilitative interventions in patients with frozen shoulder: umbrella review of systematic reviews. J Pain Res. 2022;15:2449-64.
- ↑ 48.0 48.1 48.2 48.3 48.4 48.5 Challoumas D, Biddle M, McLean M, Millar NL. Comparison of treatments for frozen shoulder: a systematic review and meta-analysis. JAMA Netw Open. 2020;3(12):e2029581.
- ↑ Kelley MJ, et al. Shoulder pain and mobility deficits: adhesive capsulitis. J Orthop Sports Phys Ther. 2013;43(5):A1-31.
- ↑ Doner G, Guven Z, Atalay A, Celiker R. Evaluation of Mulligan's technique for adhesive capsulitis of the shoulder. J Rehabil Med. 2013;45(1):87-91.
- ↑ Yang JL, Chang CW, Chen SY, Wang SF, Lin JJ. Mobilization techniques in subjects with frozen shoulder syndrome: randomized multiple-treatment trial. Phys Ther. 2007;87:1307-15.
- ↑ 52.0 52.1 Vermeulen HM, Rozing PM, Obermann WR, le Cessie S, Vliet Vlieland TP. Comparison of high-grade and low-grade mobilization techniques in the management of adhesive capsulitis of the shoulder: randomized controlled trial. Phys Ther. 2006;86:355-68.
- ↑ Johnson AJ, Godges JJ, Zimmerman GJ, Ounanian LL. The effect of anterior versus posterior glide joint mobilization on external rotation range of motion in patients with shoulder adhesive capsulitis. J Orthop Sports Phys Ther. 2007;37:88-99.
- ↑ Gaspar P, Willis B. Adhesive capsulitis and dynamic splinting: a controlled cohort study. BMC Musculoskelet Disord. 2009;10:111.
- ↑ Lee JH, Jeon HG, Yoon YJ. Effects of exercise intervention (with and without joint mobilization) in patients with adhesive capsulitis: a systematic review and meta-analysis. Healthcare (Basel). 2023;11:1504.
- ↑ Page MJ, Green S, Kramer S, et al. Manual therapy and exercise for adhesive capsulitis (frozen shoulder). Cochrane Database Syst Rev. 2014;(8):CD011275.
- ↑ Effects of scapulothoracic physical therapy on shoulder function in adhesive capsulitis: a systematic review and meta-analysis. Cureus. 2026.
- ↑ 58.0 58.1 Sung JH, Lee JM, Kim JH. The effectiveness of ultrasound deep heat therapy for adhesive capsulitis: a systematic review and meta-analysis. Int J Environ Res Public Health. 2022;19:1859.
- ↑ Reno C, et al. Extracorporeal shock wave therapy for chronic adhesive capsulitis in type 2 diabetics: a systematic review with meta-analysis. Phys Ther. 2025;105(7):pzaf074.
- ↑ 60.0 60.1 60.2 Zhang J, Zhong S, Tan T, et al. Comparative efficacy and patient-specific moderating factors of nonsurgical treatment strategies for frozen shoulder: an updated systematic review and network meta-analysis. Am J Sports Med. 2021.
- ↑ 61.0 61.1 Poku D, et al. Efficacy of hydrodilatation in frozen shoulder: a systematic review and meta-analysis. Br Med Bull. 2023;147(1):121.
- ↑ 62.0 62.1 Hydrodilatation for adhesive capsulitis: a systematic review exploring efficacy and optimal technique. 2026. PMID 42527106.
- ↑ Bal A, Eskioglu E, Gulec B, Aydog E, Gurcay E, Cakci A. Effectiveness of corticosteroid injection in adhesive capsulitis. Clin Rehabil. 2008;22:503-12.
- ↑ Jewell DV, Riddle DL, Thacker LR. Interventions associated with an increased or decreased likelihood of pain reduction and improved function in patients with adhesive capsulitis: a retrospective cohort study. Phys Ther. 2009;89:419-29.
- ↑ Tedla JS, Sangadala DR. Proprioceptive neuromuscular facilitation techniques in adhesive capsulitis: a systematic review and meta-analysis. J Musculoskelet Neuronal Interact. 2019;19(4):482-91.
- ↑ Green S, Buchbinder R, Hetrick SE. Physiotherapy interventions for shoulder pain. Cochrane Database Syst Rev. 2003;(2):CD004258.
- ↑ Buchbinder R, Green S, Youd JM. Corticosteroid injections for shoulder pain. Cochrane Database Syst Rev. 2003;(1):CD004016.
- ↑ 68.0 68.1 68.2 68.3 68.4 Neviaser AS, Hannafin JA. Adhesive capsulitis: a review of current treatment. Am J Sports Med. 2010;38:2346-56.
- ↑ Rymaruk S, Peach C. Indications for hydrodilatation for frozen shoulder. EFORT Open Rev. 2017;2(11):462-8.
- ↑ Buchbinder R, Green S, Youd JM, Johnston RV. Oral steroids for adhesive capsulitis. Cochrane Database Syst Rev. 2006;(4):CD006189.
- ↑ Boyles RE, Flynn TW, Whitman JM. Manipulation following regional interscalene anesthetic block for shoulder adhesive capsulitis: a case series. Man Ther. 2005;10:164-71.
- ↑ Quan GM, Carr D, Schlicht S, Powell G, Choong PF. Lessons learnt from the painful shoulder; a case series of malignant shoulder girdle tumours misdiagnosed as frozen shoulder. Int Semin Surg Oncol. 2005;2:2.